Every movement the human body performs depends on an intricate partnership between muscle tissue and the skeletal framework, and that partnership can fail in characteristic ways. The final lesson of this course turns from healthy anatomy to pathology, examining six disorders that the source material groups under the muscular and skeletal systems: myasthenia gravis, muscular dystrophy, tetany, arthritis, osteoporosis and gout. Each condition attacks a different link in the chain that connects nerve signal, muscle contraction, joint articulation and bone integrity, which is precisely why studying them together sharpens the understanding of how normal locomotion works.
This lesson builds directly on the preceding discussion of the appendicular skeleton and joints. Having established that joints are points of contact between bones, or between bones and cartilages, and that they act as fulcrums for muscle-generated force, the analysis now considers what happens when the neuromuscular junction falters, when muscle fibres degenerate, when calcium balance collapses, or when joint surfaces and bone mass deteriorate. The definitions and characteristic features presented here follow the source material closely, preserving its terminology and order of ideas so that learners can move confidently between the healthy and disordered states.
Because this is the closing lesson of the course, it also serves as a synthesis point. The disorders described are not isolated curiosities; each one illuminates a mechanism already studied, from the sliding of muscle filaments to the structural classification of fibrous, cartilaginous and synovial joints. A learner who can explain why low calcium produces tetany, or why falling estrogen levels correlate with osteoporosis, has genuinely internalised the physiology that precedes pathology. The sections below pair each disorder with its stated cause and features, then extend the discussion with carefully separated background notes.
On This Page
- Myasthenia Gravis: When the Neuromuscular Junction Fails
- Muscular Dystrophy: Progressive Degeneration of Skeletal Muscle
- Tetany: Calcium Deficiency and Wild Muscle Contractions
- Arthritis and Gout: Inflammation at the Joints
- Osteoporosis: Age-Related Loss of Bone Mass
- Consolidating the Six Disorders and Looking Ahead
Myasthenia Gravis: When the Neuromuscular Junction Fails
Myasthenia gravis is described as an autoimmune disorder affecting the neuromuscular junction, the specialised contact point where a motor nerve ending transmits its signal to a skeletal muscle fibre. The consequence is a triad of fatigue, weakening and paralysis of skeletal muscle. Because the junction is the gateway through which every voluntary command must pass, a fault there produces weakness that is genuinely muscular in its expression even though the underlying defect lies in communication rather than in the muscle fibres themselves. Understanding this distinction is essential for interpreting the clinical picture accurately.
The Stated Features and Their Physiological Logic
The source material lists fatigue, weakening and paralysis as the leading features of myasthenia gravis, and the sequence is instructive. Fatigue appears first because repeated signalling through a compromised junction becomes progressively less effective; weakening follows as fewer muscle fibres respond reliably to each command; and paralysis represents the extreme end of that continuum. Skeletal muscle, the tissue responsible for voluntary movement and posture, is the target throughout. Learners should note that the disorder is classified as autoimmune, meaning the body's own defence mechanisms are implicated in damaging the junctional apparatus.
Connecting this disorder to earlier lessons reinforces the architecture of locomotion. Muscles generate force, joints act as fulcrums, and bones provide leverage, but none of this proceeds without a reliable nerve-to-muscle signal. Myasthenia gravis therefore illustrates that locomotion is a system property: a defect at one small junction can degrade movement across the entire body. The characteristic pattern of fatigue worsening with activity, while not elaborated in the source text, follows naturally from the stated features and helps learners appreciate why the condition is described in terms of weakening rather than structural destruction of muscle.
Why the Junction Matters for Voluntary Movement
Voluntary movement, which the course defines as movement that causes an animal to change its place, depends on skeletal muscle contracting under conscious command. The neuromuscular junction is the relay station for that command, so its impairment directly undermines the voluntary control of posture and locomotion. Framing myasthenia gravis this way allows learners to place it alongside muscular dystrophy as a muscle-centred disorder, while recognising that the two differ fundamentally in where the primary fault lies: at the junction in one case, within the muscle fibre in the other.
For examination purposes, the essential facts are compact: autoimmune in nature, affecting the neuromuscular junction, producing fatigue, weakening and paralysis of skeletal muscle. Learners should be able to state these features precisely and to explain, in a sentence or two, why a junctional disorder manifests as muscular weakness. That explanatory step, linking location to symptom, is the kind of reasoning that distinguishes genuine understanding from memorisation and prepares the ground for comparing the remaining disorders in this lesson.
Muscular Dystrophy: Progressive Degeneration of Skeletal Muscle
Muscular dystrophy is characterised in the source material as progressive degeneration of skeletal muscle, mostly due to genetic disorder. Two elements of that definition deserve emphasis. First, the word progressive signals that the condition advances over time rather than presenting as a fixed deficit. Second, the genetic origin places the primary fault inside the muscle tissue itself, distinguishing it sharply from myasthenia gravis, where the muscle is structurally sound but poorly signalled. Together, these two muscle disorders bracket the range of muscular pathology: one communicative, one degenerative.
Features, Cause and the Meaning of Degeneration
Degeneration, in this context, means the gradual deterioration of skeletal muscle tissue, and because skeletal muscle is the effector of voluntary movement, its progressive loss translates into declining strength and movement capacity. The source material attributes most cases to genetic disorder, which means the tendency is inherited through the genetic material rather than acquired through injury or infection. Learners should retain the qualifier "mostly," since it acknowledges that genetic causation accounts for the majority but not necessarily all instances, a precision worth preserving in written answers.
Placing muscular dystrophy beside the healthy muscle physiology studied earlier makes the pathology vivid. Normal contraction depends on intact muscle fibres with organised contractile filaments; progressive degeneration erodes that substrate, so even a perfectly delivered nerve signal finds less functional tissue to activate. The result is weakness that worsens as degeneration advances. This is why the disorder is described as progressive rather than episodic, and why it belongs firmly among the disorders of the muscular system rather than among joint or bone conditions.
Contrasting the Two Muscle Disorders
A comparison table clarifies the distinction that examiners frequently test. Myasthenia gravis is autoimmune and junctional, with fatigue, weakening and paralysis of skeletal muscle; muscular dystrophy is genetic and intrinsic to the muscle, with progressive degeneration of skeletal muscle. Both ultimately weaken skeletal muscle, yet their causes, sites of primary fault and trajectories differ. Holding both profiles in mind simultaneously is a useful revision technique, because it forces the learner to articulate what each disorder is not as well as what it is.
This contrast also has diagnostic value in principle. A clinician confronted with muscular weakness must ask whether the problem lies in signal transmission or in the muscle tissue itself, and the two disorders in this section represent those two possibilities. The source material does not elaborate on diagnosis, and this lesson does not extend beyond it; the point is simply that the definitions themselves encode the crucial distinction. Learners who can reproduce the definitions accurately and explain the difference in their own words have met the requirement comfortably.
Tetany: Calcium Deficiency and Wild Muscle Contractions
Tetany is defined as rapid spasms, described in the source material as wild contractions, in muscle due to low Ca^{++} in body fluid. The definition is compact but rich: it names the observable phenomenon, the spasms; characterises their quality, wild and rapid; and identifies the cause, a deficiency of calcium ions in the body fluids. Unlike the two preceding disorders, tetany is not autoimmune or genetic in origin but metabolic, arising from an ionic imbalance. This makes it an excellent illustration of how tightly muscle function is coupled to the chemical environment surrounding the tissue.
The Stated Cause and the Meaning of Wild Contractions
The phrase "wild contractions" captures the involuntary, uncontrolled character of the spasms. Normal muscle contraction is disciplined: it occurs when commanded, produces graded force, and relaxes afterwards. In tetany, the low concentration of calcium ions in body fluid removes a restraining influence, and muscles fire in rapid, uncontrolled spasms. The source material does not elaborate the ionic mechanism further, and this lesson stays within its stated boundaries; what matters for the learner is the causal chain from low Ca^{++} to rapid spasms, stated clearly and reproducibly.
Calcium's role here connects naturally to earlier course content on muscle contraction, where the interplay of ions underlies the contractile process. Tetany demonstrates that the correct ionic milieu is as important as intact structure: a muscle can be anatomically sound and genetically normal, yet still malfunction violently if the fluid bathing it is depleted of calcium. Learners should be able to state the definition, identify the ion involved, and distinguish tetany from the muscle disorders already discussed by its metabolic rather than structural or autoimmune origin.
Placing Tetany Among the Disorders
Within the lesson's sequence, tetany occupies a distinct position. Myasthenia gravis and muscular dystrophy concern the signalling and substance of muscle respectively; tetany concerns the chemical environment in which muscle operates. This three-way distinction, junction, tissue and milieu, provides a memorable framework for revision. Each disorder in the muscular group can be assigned to one of these categories, and the assignment itself demonstrates understanding of what the source material says about each condition's cause.
For written answers, the essential content is the definition with its cause: rapid spasms, or wild contractions, in muscle due to low Ca^{++} in body fluid. Precision about the ion and its location, body fluid rather than bone or cell interior, matters. Learners who reproduce this definition accurately and can explain in a sentence why calcium depletion produces uncontrolled contraction have satisfied the requirement. The next section shifts from muscle to joint pathology, beginning with arthritis and gout.
Arthritis and Gout: Inflammation at the Joints
Arthritis is defined simply as inflammation of joints, and gout as inflammation of joints due to accumulation of uric acid crystals. The two definitions share their core term, inflammation of joints, but differ in causation: arthritis is stated generically, while gout specifies the accumulation of uric acid crystals as its trigger. This pairing is pedagogically useful because it shows how a general category and a specific member of that category can be defined side by side. Both conditions attack the joints that earlier lessons established as the fulcrums of movement.
Arthritis: The General Definition
Because joints are the points of contact between bones, or between bones and cartilages, through which muscle-generated force produces movement, inflammation at these points directly compromises locomotion. The source material defines arthritis as inflammation of joints without further qualification, and this lesson respects that brevity. Learners should note that the definition is deliberately general: it names the site and the pathological process, inflammation, and leaves the specific varieties and their individual causes outside its scope. Reproducing the definition faithfully is the examination requirement.
The connection to joint structure is worth drawing out. The course has classified joints into fibrous, cartilaginous and synovial forms, with synovial joints permitting considerable movement and serving locomotion. Joints that move are the ones most exposed to the mechanical demands of movement, and inflammation there is felt most acutely during activity. The source material does not make this inference explicitly, but it follows from the established anatomy and helps learners appreciate why joint inflammation matters so much for an animal whose voluntary movement changes its place.
Gout: Uric Acid Crystals in the Joints
Gout sharpens the general definition by naming a cause: inflammation of joints due to accumulation of uric acid crystals. The crystals are the irritant, and their accumulation within the joint provokes the inflammatory response. This makes gout a useful contrast with arthritis as stated: same site, same process, but a specified trigger. Learners should be able to state both definitions and to explain that gout is a form of joint inflammation with a defined crystalline cause, while arthritis as defined in the source material is joint inflammation without a stated cause.
For revision, the pair can be memorised as a hierarchy: all gout involves joint inflammation, but the general definition of arthritis does not specify uric acid. The distinction rewards careful reading. It also prepares the ground for the final disorder in the lesson, osteoporosis, which shifts attention from the joint to the bone itself. Together, arthritis, gout and osteoporosis complete the skeletal side of the lesson, complementing the muscular disorders that opened it.
Osteoporosis: Age-Related Loss of Bone Mass
Osteoporosis is described as an age-related disorder characterised by decreased bone mass and increased chances of fractures, with decreased levels of estrogen identified as a common cause. The definition contains three elements that learners should reproduce: the age-related nature of the disorder, the reduction in bone mass, and the elevated fracture risk that follows from it. The stated cause, decreased estrogen levels, is offered as a common rather than universal explanation, a qualifier that should be preserved in written answers.
Features and the Stated Cause
Decreased bone mass is the central feature, and increased chances of fractures follow logically from it: less bone substance means weaker bone, and weaker bone fails under forces that healthy bone would withstand. The source material frames the disorder as age-related, placing it among the conditions that accompany ageing rather than among infections, injuries or inherited defects. Decreased levels of estrogen are named as a common cause, which links the disorder to hormonal status while leaving room for other contributing factors that the source material does not enumerate.
Within the lesson's framework, osteoporosis completes the skeletal picture. Arthritis and gout concern the joints, the points of contact and fulcrums of movement; osteoporosis concerns the bones themselves, the levers that muscles move. A skeleton whose mass has declined provides poorer leverage and greater fracture risk, so the mechanical consequences for locomotion are direct. Learners should be able to state the definition, list the two characteristic features, and name decreased estrogen levels as the common cause identified in the material.
Connecting Bone Health to the Skeletal System
The course has already surveyed the axial and appendicular skeleton, the bony framework that supports the body and provides attachment for muscles. Osteoporosis attacks that framework by reducing its mass, and the increased fracture risk is the practical consequence. Because the skeleton serves both support and leverage, its weakening affects posture and movement together. This is why osteoporosis belongs in a lesson on locomotion and movement: the disorder degrades the very structure through which muscle force is transmitted to produce motion.
For revision, the osteoporosis entry is best memorised as a triad: age-related, decreased bone mass, increased fracture chances, with decreased estrogen as the common cause. Learners should also be able to distinguish it from arthritis and gout by site: bone rather than joint. That single distinction, bone versus joint, organises the skeletal half of the lesson neatly and mirrors the earlier distinction between junction, tissue and milieu in the muscular half.
Consolidating the Six Disorders and Looking Ahead
The six disorders now form a coherent map of muscular and skeletal pathology. Myasthenia gravis strikes the neuromuscular junction; muscular dystrophy degenerates the muscle tissue; tetany disrupts the ionic environment of muscle; arthritis inflames the joints; gout inflames the joints through uric acid crystal accumulation; and osteoporosis reduces bone mass with age. Each entry in the source material follows the same economical pattern, naming the disorder, its characteristic features and, where stated, its cause. Reproducing that pattern accurately is the core examination skill this lesson develops.
A Comparative Framework for Revision
The most efficient revision strategy is to sort the six disorders by the component of the locomotor system they affect. The muscular group comprises myasthenia gravis, muscular dystrophy and tetany; the skeletal group comprises arthritis, gout and osteoporosis, with the first two centred on joints and the third on bone. Within the muscular group, the causes differ instructively: autoimmune, genetic and metabolic respectively. Within the skeletal group, the causes range from unspecified inflammation to uric acid crystals to hormonal change with age. This sorting exercise converts six separate definitions into one structured body of knowledge.
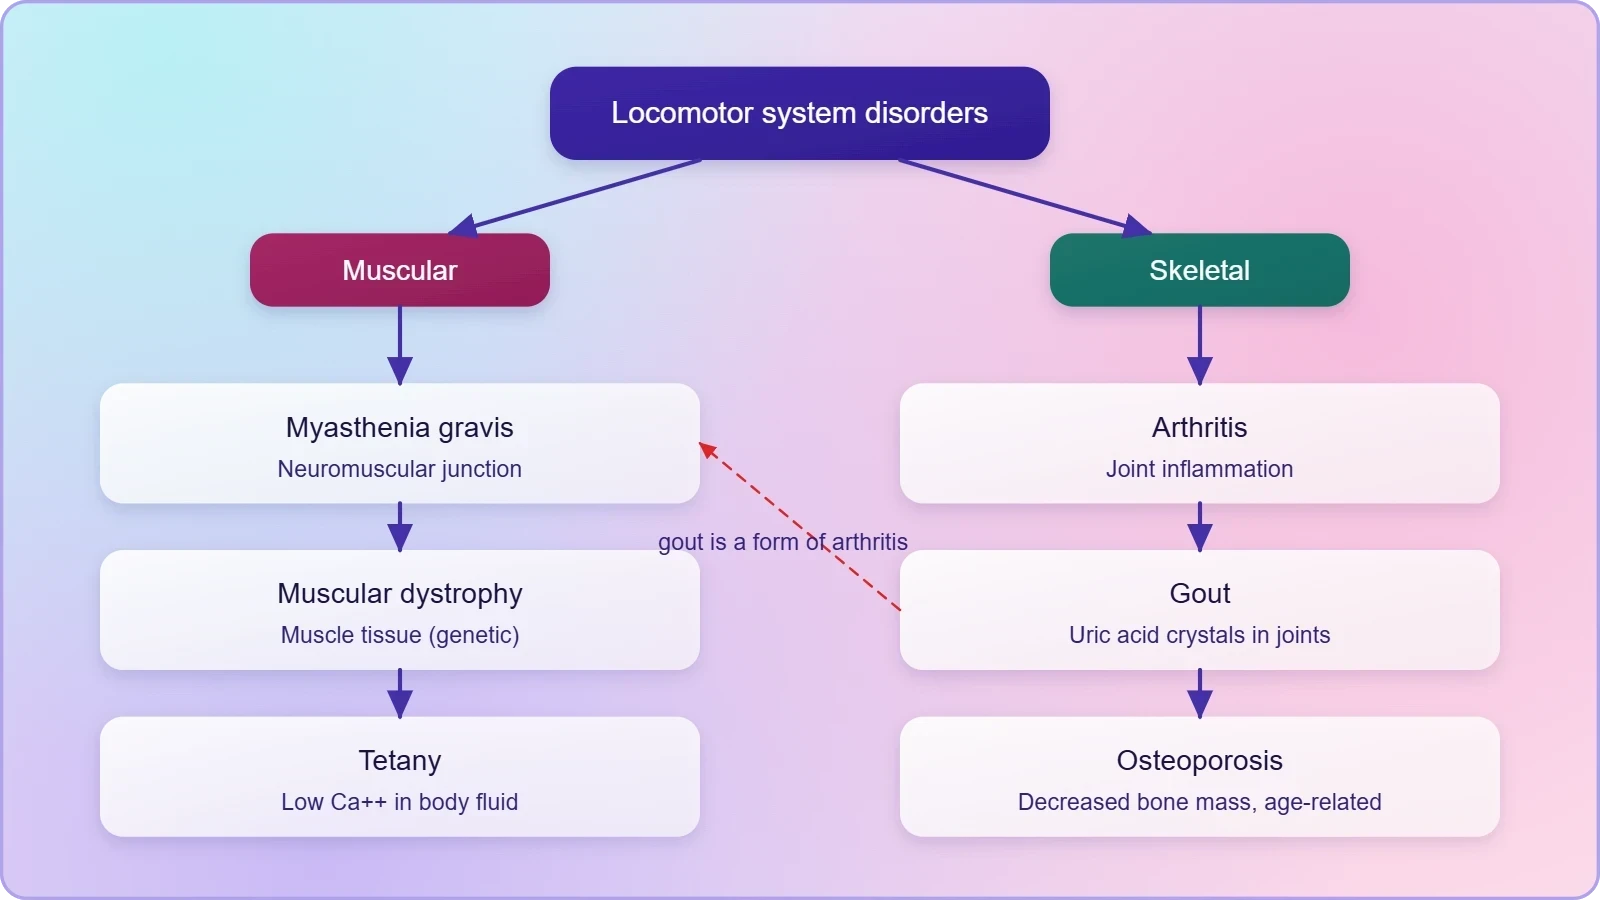
Learners should also practise stating each definition in the source material's own terms before paraphrasing. Myasthenia gravis is an autoimmune disorder affecting the neuromuscular junction leading to fatigue, weakening and paralysis of skeletal muscle. Muscular dystrophy is progressive degeneration of skeletal muscle mostly due to genetic disorder. Tetany consists of rapid spasms in muscle due to low Ca^{++} in body fluid. Arthritis is inflammation of joints. Osteoporosis is an age-related disorder with decreased bone mass and increased fracture chances, commonly caused by decreased estrogen. Gout is inflammation of joints due to accumulation of uric acid crystals.
Going Further
Two pieces of well-established background deepen the picture without altering it. First, autoimmune disorders occur when the body's immune system attacks its own tissues; this general principle explains why myasthenia gravis, an autoimmune condition, damages the body's own neuromuscular junction and produces the fatigue, weakening and paralysis described. Second, uric acid is a waste product that can form crystals in joints, causing gout; this clarifies the mechanism behind the accumulation named in the definition. Both notes are background context, offered separately from the source material's own statements.
With this lesson the course concludes. The progression from types of movement through muscle structure, the axial and appendicular skeleton, and the three structural forms of joints has now arrived at the disorders that afflict these systems. A learner who can define all six conditions, state their causes where given, and locate each within the muscular or skeletal framework has completed the course's arc. The final consolidation table below gathers the essential facts for last-minute revision before examinations.
Also Read
- No links available.
From our network :
- 98% of Global MBA Programs Now Prefer GRE Over GMAT Focus EditionExplore why 98% of global MBA programs now prefer the GRE over GMAT Focus. Learn about the shorter GRE format, verbal logic importance, and strategic versatility for students.
- AI-Powered 'Precision Diagnostic' Replaces Standard GRE Score ReportsDiscover the new GRE Precision Diagnostic. Learn how AI-powered behavioral analytics and time-to-solve tracking are replacing standard GRE score reports to empower students.
- EV 2.0: The Solid-State Battery Breakthrough and Global Factory ExpansionDiscover the impact of the Solid-State Battery Breakthrough on the EV market. Learn about CATL and BYD stock growth, global factory expansion in Europe, and the future of EV 2.0 technology.
- Trump Political Strategy How Geopolitical Stunts Serve As Media Diversions
- Mastering DB2 12.1 Instance Design: A Technical Deep Dive into Modern Database ArchitectureComprehensive guide to DB2 12.1 Instance Design. Explore architectural components, HADR setup, buffer pool tuning, and security policies for IBM DB2 12.1. Includes 10 functional SQL and Shell samples.
- Vite 6/7 'Cold Start' Regression in Massive Module GraphsIn-depth analysis of Vite 6/7 cold start regressions in massive module graphs. Learn about barrel file issues, pre-bundling optimizations, and how to improve Vite dev server performance.
- 10 Physics Numerical Problems with Solutions for IIT JEEPrepare for IIT JEE with 10 physics numerical problems, complete with detailed solutions and conceptual explanations. Ideal for mastering kinematics, thermodynamics, electromagnetism, and optics.
- Mastering DB2 LUW v12 Tables: A Comprehensive Technical GuideComprehensive guide on DB2 LUW v12 tables. Explore CREATE TABLE syntax, BLU Acceleration, range partitioning, data types, and security features for IBM DB2 LUW v12.
- Analyzing Trump Deportation Numbers Insights Into The 2026 Immigration Crackdown
RESOURCES
- Disorders Muscular And Skeletal System - BYJU'Sbyjus.comList of Disorders · Myasthenia gravis: It is the abnormal weakening and rapid fatigue of certain muscles. · Muscular Dystrophy: This is mostly hereditary.
- Muscle & Bone Diseases | NIAMSniams.nih.govJun 6, 2025 ... What is osteopetrosis? It is a rare disorder that causes bones to grow abnormally and become too dense. When this…
- Muscular dystrophy - Symptoms and causes - Mayo Clinicmayoclinic.orgMay 17, 2025 ... Muscular dystrophy is a group of diseases that causes muscles to become weaker and lose mass over time. The condition…
- Muscular Dystrophy | National Institute of Neurological Disorders ...ninds.nih.gov... diseases that cause progressive weakness and degeneration of skeletal muscles ... Rule out disorders of the central and/or peripheral nervous systems ...
- 1.00 Musculoskeletal Disorders - Adult | Disability | SSAssa.govThese disorders may involve the bones or major joints; or the tendons, ligaments, muscles, or other soft tissues. 2. We evaluate soft tissue injuries…
- Muscle Disorders | MedlinePlusmedlineplus.govDec 10, 2024 ... Your muscles help you move and help your body work. Muscle disorders can cause weakness, pain or even paralysis. Read…
- Skeletal System: What It Is, Function, Care & Anatomymy.clevelandclinic.orgJan 10, 2024 ... The skeletal system is your body's support structure. Its parts include your bones, muscles, cartilage and connective tissue like ligaments ...
- Musculoskeletal disorders: an evolving view of multi-tissue ... - PMCpmc.ncbi.nlm.nih.govThe multi-tissue integrated system is affected by many skeletal muscle diseases, which disrupt tissue contact. More than 150 diseases affect muscles, bones ...
- Skeletal Muscle (Striated Muscle): What It Is & Functionmy.clevelandclinic.orgApr 14, 2025 ... Your skeletal muscles are located between the bones (skeletal system) throughout your body. ... (diseases that affect skeletal muscles). A ...
- Musculoskeletal Disorders - Selected Health Conditions and ... - NCBIncbi.nlm.nih.govMusculoskeletal disorders comprise diverse conditions affecting bones, joints, muscles, and connective tissues. These disorders may result in pain and loss ...
- Bone, Joint, and Muscle Disorders - Merck Manual Consumer Versionmerckmanuals.comSkeletal. Smooth. Cardiac (heart). Two of these kinds—skeletal and smooth—are part of the musculoskeletal system. Muscular System. 3D Model. Skeletal muscle is ...
- Physiology, Skeletal Muscle - StatPearls - NCBI Bookshelf - NIHncbi.nlm.nih.govJul 30, 2023 ... Multiple types of skeletal muscle disorders have been studied, including muscular ... Skeletal muscle is found throughout the body, attached…
- Regulation and physiological roles of the calpain system ... - PubMedpubmed.ncbi.nlm.nih.govOct 1, 2012 ... Regulation and physiological roles of the calpain system in muscular disorders ... skeletal muscle against stress. This review summarizes ...
- What to know about musculoskeletal disorders - Medical News Todaymedicalnewstoday.comMuscular dystrophy: A group of genetic conditions that slowly cause the muscles to weaken over time. · Sarcopenia: The age-related loss of skeletal muscle…
- Musculoskeletal Disorders (MSDs) - CCOHSccohs.caTendon Injury. Tendons consist of numerous bundles of fibres that attach muscles to bones. Tendon disorders related to repetitive or frequent work activities ...