The menstrual cycle is far more than a monthly calendar event; it is a precisely orchestrated endocrine conversation between the brain and the ovaries that prepares the female body for the possibility of pregnancy roughly every four weeks. Beginning at puberty with a first menstruation called menarche and ceasing around the age of fifty at menopause, this cycle is one of the clearest outward indicators that the reproductive system is functioning normally. Understanding it requires us to move beyond memorising a list of phases and instead see how pituitary hormones and ovarian steroids continuously adjust one another in a feedback loop of remarkable sensitivity.
This lesson examines the four phases of the cycle — menstrual, follicular, ovulatory and luteal — and traces the hormonal signals that drive each one. We will follow follicle-stimulating hormone and luteinising hormone from the anterior pituitary, watch oestrogen rise as follicles mature, and see how a sudden surge of luteinising hormone triggers ovulation. We will then study how the corpus luteum sustains the uterine lining with progesterone, and why its degeneration brings the cycle back to its starting point. Along the way, we connect these events to the ovarian changes described in earlier lessons on oogenesis.
Because the menstrual cycle sits at the intersection of anatomy, endocrinology and clinical medicine, it rewards careful study. We will clarify the positive feedback that produces the mid-cycle surge, examine why the familiar 28-day figure is only an average, and address the hormonal logic behind menstruation itself. By the end, you should be able to explain not just what happens in each phase, but why it happens and what would go wrong if any link in the chain failed.
On This Page
The Menstrual Cycle as a Coordinated Endocrine Rhythm
The reproductive cycle in female primates — monkeys, apes and human beings — is called the menstrual cycle, and it is defined by the periodic shedding of the uterine lining. In human females, menstruation recurs at an average interval of about 28 or 29 days, and the sequence of events from one menstruation to the next constitutes one complete cycle. Crucially, this cycle is not a single process but two interlocking ones: a cycle of follicular development within the ovary and a cycle of endometrial preparation within the uterus, synchronised by hormones.
The control centre lies in the hypothalamus and anterior pituitary, which secrete gonadotropins — luteinising hormone (LH) and follicle-stimulating hormone (FSH) — that act on the ovary. The ovary, in turn, returns oestrogen and progesterone to the bloodstream, and these steroids feed back on the hypothalamus and pituitary to modulate gonadotropin release. This two-way communication ensures that follicular growth, ovulation and uterine preparation occur in the correct order and at the correct time.
Two Cycles Running in Parallel
The ovarian cycle describes changes in the follicle and is divided into the follicular phase, ovulation and the luteal phase. The uterine cycle describes changes in the endometrium and is divided into menstruation, the proliferative phase and the secretory phase. These two cycles are not independent; each phase of the uterine cycle is a direct consequence of the hormonal output of the corresponding ovarian phase, which is why clinicians often read the state of the endometrium as a mirror of ovarian activity.
Recognising this parallelism prevents a common confusion. Students sometimes treat the follicular phase and the proliferative phase as the same event, but one occurs in the ovary and the other in the uterus. The follicular phase is the growth of the follicle under FSH; the proliferative phase is the thickening of the endometrium under oestrogen. They coincide in time, but they are anatomically distinct processes driven by the same hormonal signal.
Hormones as the Language of the Cycle
Four hormones dominate the narrative: FSH, LH, oestrogen and progesterone. FSH from the anterior pituitary stimulates follicular development and, in the growing follicle, promotes the secretion of oestrogen. LH triggers ovulation and later maintains the corpus luteum. Oestrogen, produced by granulosa cells of growing follicles, drives endometrial proliferation and, at high sustained levels, provokes the LH surge. Progesterone, produced by the corpus luteum, converts the endometrium into a secretory tissue ready for implantation.
Each hormone has a characteristic signature on a cycle graph, and reading these signatures is a core exam skill. FSH rises early in the follicular phase and peaks mid-cycle; LH stays low until a sharp mid-cycle spike; oestrogen climbs through the follicular phase, peaks just before ovulation, dips, then rises again in the luteal phase; progesterone remains low until ovulation and then climbs to a broad luteal peak. Learning to interpret these curves is as important as memorising the phase names.
The Menstrual Phase: Shedding and Renewal
The cycle begins with the menstrual phase, during which menstrual flow occurs and lasts for three to five days. This flow results from the breakdown of the endometrial lining of the uterus and its blood vessels, forming a liquid that passes out through the vagina. Menstruation occurs only if the released ovum has not been fertilised; if fertilisation and implantation have taken place, the endometrium is retained and the cycle is suspended. The shedding is therefore a signal of a cycle that did not result in pregnancy.
The hormonal trigger for menstruation is the withdrawal of progesterone and oestrogen as the corpus luteum degenerates at the end of the previous cycle. Without these steroids to sustain it, the endometrium can no longer be maintained, its blood vessels constrict, and the functional layer is shed. This is why menstruation is best understood as a withdrawal bleed: it is the consequence of falling hormone levels rather than the direct action of any single hormone.
What Menstrual Blood Contains
Menstrual fluid is not simply blood. It contains endometrial tissue fragments, blood, mucus and vaginal secretions, and it normally does not clot because the endometrium releases fibrinolytic enzymes that break down clots as they form. The volume of flow is typically modest, and the duration of three to five days reflects the time needed for the entire functional layer to be shed and for repair to begin. Recognising this composition helps explain why the flow is described as a liquid rather than as clotted blood.
The absence of menstruation, called amenorrhoea, may indicate pregnancy, but it can also arise from stress, poor health, excessive exercise, low body weight or endocrine disorders. This is an important clinical point: a missed period is a prompt for investigation, not an automatic diagnosis. The menstrual phase, in other words, is both a physiological reset and a useful diagnostic window into the broader hormonal state of the body.
Why Menstruation Is Not a Disease
A persistent misconception treats menstruation as a disorder or an impurity, but it is a normal physiological process. The endometrium is built up each cycle in anticipation of implantation, and when implantation does not occur, shedding it is the most efficient way to reset the tissue for the next opportunity. The process is regulated, predictable in its broad timing, and essential to reproductive function. Framing it correctly matters for both scientific understanding and for the hygiene and health discussions that follow in the next lesson.
It is also worth noting that the first menstruation, menarche, marks the onset of reproductive capability, while its permanent cessation, menopause, marks the end. The span between them — the reproductive years — is characterised by cyclic menstruation, and the presence of regular cycles is a reliable indicator that the hypothalamic-pituitary-ovarian axis is functioning normally. Irregularity, by contrast, invites a closer look at that axis.
The Follicular Phase: Growth Under FSH
The menstrual phase is followed by the follicular phase, during which primary follicles in the ovary grow to become a fully mature Graafian follicle, while simultaneously the endometrium regenerates through proliferation. These coordinated changes in ovary and uterus are induced by shifts in the levels of pituitary and ovarian hormones. The secretion of gonadotropins, LH and FSH, increases gradually during this phase, stimulating follicular development and the secretion of oestrogens by the growing follicles.
At the start of the follicular phase, several primary follicles are recruited, but only one typically reaches full maturity; the rest undergo atresia. This selection is driven by competition for limited FSH, and the follicle that develops the most FSH receptors and produces the most oestrogen gains a survival advantage. The surviving follicle becomes the dominant follicle, and it is this structure that will eventually ovulate. The follicular phase is therefore a phase of selection as much as of growth.
From Primary Follicle to Graafian Follicle
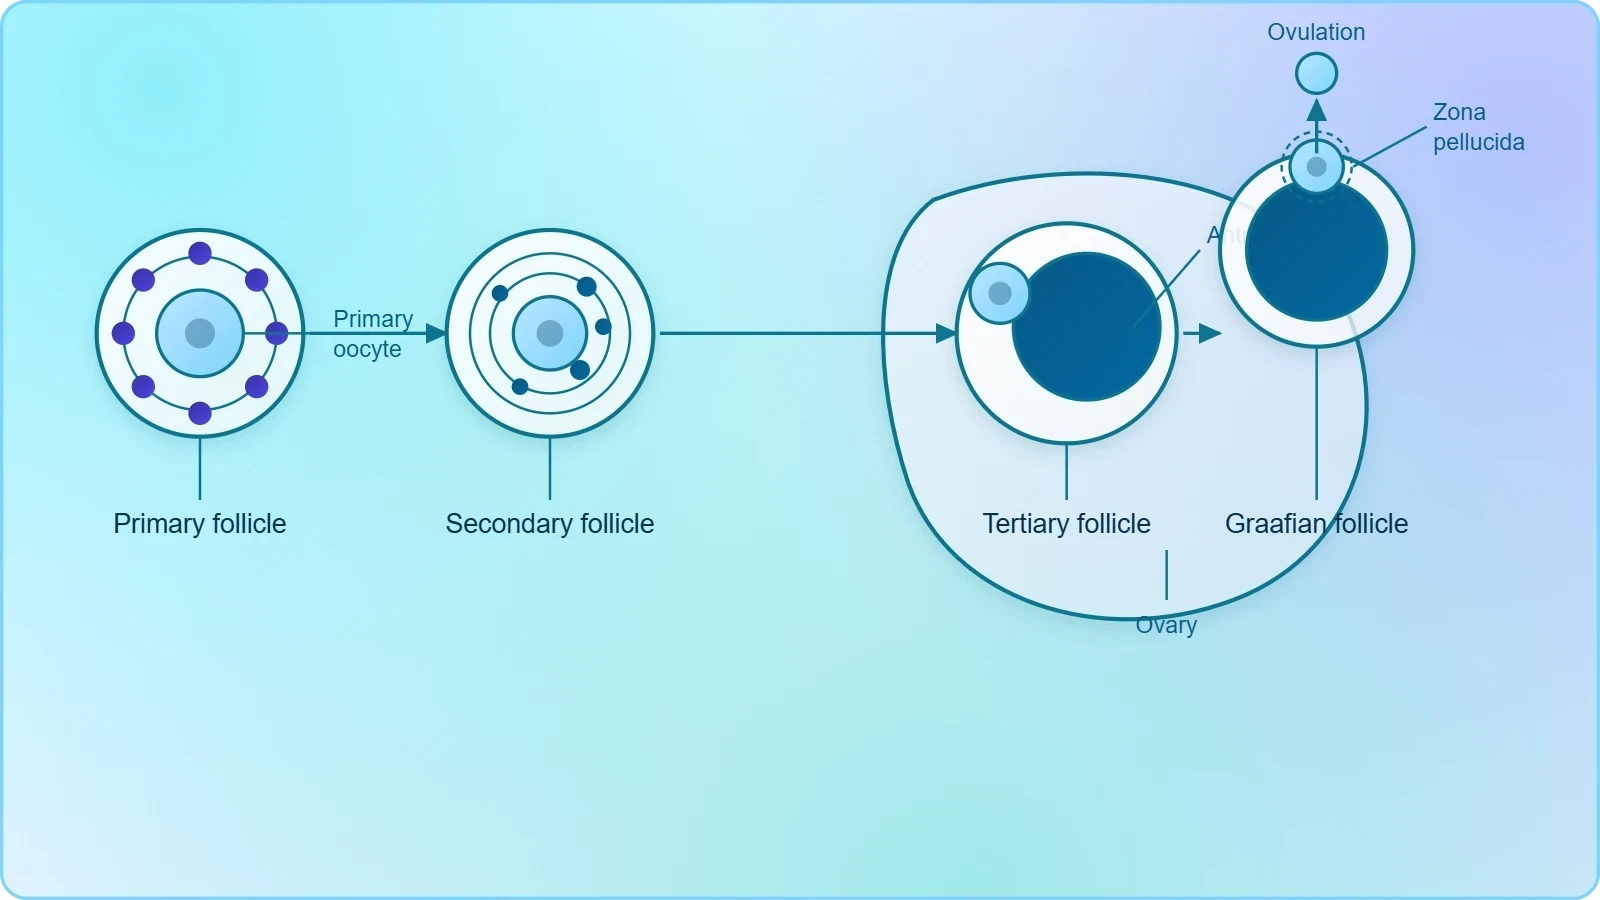
The stages of follicular development build directly on the oogenesis sequence studied earlier. A primary follicle, consisting of a primary oocyte surrounded by a layer of granulosa cells, develops into a secondary follicle with additional granulosa layers and a theca. It then becomes a tertiary follicle, characterised by a fluid-filled cavity called the antrum, with the theca organised into an inner theca interna and an outer theca externa. Within the tertiary follicle, the primary oocyte completes its first meiotic division, producing a secondary oocyte and a first polar body.
The tertiary follicle then transforms into the mature or Graafian follicle, and the secondary oocyte forms a new membrane called the zona pellucida around itself. The Graafian follicle is a large, fluid-filled structure that bulges from the surface of the ovary and is poised to rupture. The entire progression from primary to Graafian follicle unfolds over roughly the first half of the cycle, driven by rising FSH and supported by locally produced growth factors and steroids.
Oestrogen and Endometrial Proliferation
As the dominant follicle grows, its granulosa cells secrete increasing amounts of oestrogen, principally oestradiol. This oestrogen acts on the endometrium to stimulate proliferation, thickening the lining and rebuilding its glands and blood vessels after the previous menstruation. This is the proliferative phase of the uterine cycle, and it is entirely dependent on the rising oestrogen output of the follicle. If the follicle fails to develop, the endometrium cannot proliferate, and the cycle stalls.
Oestrogen also exerts feedback on the pituitary, but the nature of that feedback changes with concentration. At moderate levels, oestrogen suppresses FSH release, which helps ensure that only the dominant follicle continues to grow. At high, sustained levels, however, the feedback switches from negative to positive, and this switch is the key to the next phase of the cycle. Understanding this concentration-dependent behaviour is essential to explaining ovulation.
The Ovulatory Phase and the LH Surge
Both LH and FSH attain a peak level in the middle of the cycle, around the fourteenth day in a typical 28-day cycle. The rapid secretion of LH that reaches its maximum at mid-cycle is called the LH surge, and it is this surge that induces rupture of the Graafian follicle and the release of the ovum — the process of ovulation. Ovulation therefore marks the transition from the follicular to the luteal phase and is the single most dramatic endocrine event of the cycle.
The LH surge is not a spontaneous pituitary event; it is triggered by positive feedback from high oestrogen levels. As the dominant follicle matures, its oestrogen output rises to a sustained high concentration for roughly a day or more, and this sustained high level flips the hypothalamic-pituitary response from inhibition to stimulation. The result is a burst of gonadotropin-releasing hormone from the hypothalamus, followed by a massive release of LH from the anterior pituitary. This positive feedback loop is one of the few clear examples of positive feedback in human physiology.
Mechanism of Follicular Rupture
The LH surge sets off a cascade within the follicle. It stimulates the resumption of meiosis in the secondary oocyte, which completes its second meiotic division only upon fertilisation. It also promotes the production of enzymes and inflammatory mediators that weaken the follicular wall at the stigma, the point where the follicle will rupture. The follicle swells, the wall gives way, and the secondary oocyte, surrounded by the zona pellucida and cumulus cells, is released into the peritoneal cavity near the fimbriae of the fallopian tube.
The released oocyte is then swept into the fallopian tube, where it is transported toward the ampullary region. If sperm are present, fertilisation can occur there. The timing is tight: the oocyte remains viable for only about a day, and sperm viability in the female tract is limited to a few days. This narrow window explains why not every act of intercourse leads to fertilisation, a point that connects directly to the next lesson on fertilisation and implantation.
Reading the Mid-Cycle Signals
Clinically, the LH surge can be detected in urine, which is the basis of ovulation predictor kits used by couples trying to conceive. Some women also notice mittelschmerz, a mild one-sided pelvic pain at ovulation, or a change in cervical mucus to a clearer, stretchier consistency. Basal body temperature rises slightly after ovulation because progesterone has a thermogenic effect. These observable signs are useful because they allow the abstract hormonal graph to be correlated with real bodily changes.
It is important to stress that ovulation does not always occur on day fourteen. In a 28-day cycle it falls near the midpoint, but in longer or shorter cycles the timing shifts, and the luteal phase is relatively constant at about fourteen days while the follicular phase varies. This is why counting days from the start of menstruation is an unreliable method for predicting ovulation in individuals with irregular cycles.
The Luteal Phase and Progesterone
Ovulation is followed by the luteal phase, during which the remaining parts of the Graafian follicle transform into the corpus luteum. The corpus luteum secretes large amounts of progesterone, which is essential for the maintenance of the endometrium. Such an endometrium is necessary for implantation of the fertilised ovum and for the other events of pregnancy. The luteal phase is therefore the phase of preparation, converting the proliferated endometrium into a secretory tissue rich in glands and nutrients.
Progesterone is the dominant hormone of this phase. It thickens the endometrial lining further, increases its glandular secretion, and stabilises the tissue so that a blastocyst can implant. It also suppresses FSH and LH release, preventing the development of new follicles while the corpus luteum is active. This negative feedback ensures that no second ovulation occurs during the same cycle, preserving the single-ovum-per-cycle pattern characteristic of human reproduction.
If Fertilisation Occurs
If fertilisation occurs and the embryo implants, it secretes human chorionic gonadotropin (hCG), which rescues the corpus luteum from degeneration and sustains its progesterone output. During pregnancy, all events of the menstrual cycle stop and there is no menstruation, because the hormonal environment is continuously maintained by the corpus luteum and later by the placenta. This is why a missed period is an early sign of pregnancy and why hCG is the target of pregnancy tests.
The sustained progesterone also prepares the mammary glands for lactation and contributes to the broader physiological changes of pregnancy. The key point for this lesson is that the luteal phase is not a fixed dead end; it is a conditional phase whose outcome depends on whether implantation occurs. The same hormonal machinery that prepares the endometrium can either be maintained for nine months or dismantled within a couple of weeks.
If Fertilisation Does Not Occur
In the absence of fertilisation, the corpus luteum degenerates. This causes a fall in progesterone and oestrogen, which in turn causes disintegration of the endometrium, leading to menstruation and marking the start of a new cycle. The fall in steroid levels also releases the hypothalamus and pituitary from negative feedback, allowing FSH to rise again and recruit a new cohort of follicles. The cycle thus closes the loop and restarts automatically.
The lifespan of the corpus luteum is about fourteen days if it is not rescued by hCG. This fixed duration is why the luteal phase is relatively constant across individuals, and why variation in cycle length is almost entirely due to variation in the follicular phase. Understanding this asymmetry is a useful diagnostic principle: a short cycle usually reflects a short follicular phase, not a short luteal phase.
Feedback Control, Variation and Clinical Perspective
The menstrual cycle is a textbook illustration of feedback control in physiology. Negative feedback dominates for most of the cycle, keeping gonadotropin levels in check as ovarian steroids rise. Positive feedback appears briefly at mid-cycle, when high oestrogen drives the LH surge. The system then returns to negative feedback during the luteal phase as progesterone rises. This alternation between negative and positive feedback is what gives the cycle its characteristic rhythm and its self-correcting stability.
It is essential to recognise that the average cycle length of 28 or 29 days is just that — an average. Normal cycles vary widely, commonly between about 21 and 35 days, and can differ from one individual to another and from one cycle to another in the same individual. Stress, illness, travel, changes in body weight and intense exercise can all shift the timing. Treating 28 days as a rigid rule is a common mistake that leads to unnecessary anxiety and inaccurate predictions.
Disorders of the Cycle
When the feedback loop is disrupted, the cycle can become irregular or cease altogether. Polycystic ovary syndrome, thyroid dysfunction, hyperprolactinaemia and primary ovarian insufficiency are among the conditions that disturb the hormonal dialogue. Anovulation — failure to ovulate — is a common cause of infertility and often presents as irregular or absent periods. These clinical connections show why a solid grasp of the normal cycle is the foundation for understanding its disorders.
Menopause, the permanent cessation of menstrual cycles around the age of fifty, reflects the depletion of ovarian follicles. As follicles become scarce, oestrogen output falls, the positive feedback needed for the LH surge weakens, and cycles become irregular before stopping. The hormonal changes of menopause — falling oestrogen and relatively elevated gonadotropins — are the logical endpoint of the same feedback system that governs the cycle throughout reproductive life.
Common Misconceptions to Correct
Several misconceptions surround the cycle. One is that menstruation is the body's way of cleansing itself; in fact, it is the shedding of a lining built for implantation. Another is that ovulation always occurs on day fourteen; as we have seen, timing varies with cycle length. A third is that a cycle must be exactly 28 days to be normal; the range is much wider. Correcting these errors is not pedantry — it prevents misdiagnosis and supports informed health decisions.
A fourth misconception is that the cycle is purely reproductive in function. In reality, the same hormones influence bone density, cardiovascular health and mood, which is why cycle disturbances can have effects beyond fertility. Recognising this broader role reinforces the value of understanding the endocrine control of the cycle, and it sets the stage for the next lesson, which addresses menstrual hygiene and the misconceptions that surround it.
Also Read
- No links available.
From our network :
- Do You Need a New Router or Is Your Internet Plan the Problem?A practical comparison of the signs that point to router limits versus signs your broadband speed or provider is the bottleneck, so you can decide what to replace before spending money.
- EV 2.0: The Solid-State Battery Breakthrough and Global Factory ExpansionDiscover the impact of the Solid-State Battery Breakthrough on the EV market. Learn about CATL and BYD stock growth, global factory expansion in Europe, and the future of EV 2.0 technology.
- 10 Physics Numerical Problems with Solutions for IIT JEEPrepare for IIT JEE with 10 physics numerical problems, complete with detailed solutions and conceptual explanations. Ideal for mastering kinematics, thermodynamics, electromagnetism, and optics.
- Trump Political Strategy How Geopolitical Stunts Serve As Media Diversions
- Where to Put Your Wireless Router for Better CoverageA practical, physics-grounded guide to router placement: why the centre of the home beats the corner, how walls and metal sap signal, and how to run a simple survey that proves the improvement.
- AI-Powered 'Precision Diagnostic' Replaces Standard GRE Score ReportsDiscover the new GRE Precision Diagnostic. Learn how AI-powered behavioral analytics and time-to-solve tracking are replacing standard GRE score reports to empower students.
- Analyzing Trump Deportation Numbers Insights Into The 2026 Immigration Crackdown
- How to Print Cheaply: Cutting the Cost per PageA practical, measured guide to lowering what each printed page costs — duplex and draft modes, third-party ink, yield mathematics, and knowing when a new printer beats refills.
- 98% of Global MBA Programs Now Prefer GRE Over GMAT Focus EditionExplore why 98% of global MBA programs now prefer the GRE over GMAT Focus. Learn about the shorter GRE format, verbal logic importance, and strategic versatility for students.
RESOURCES
- The Normal Menstrual Cycle and the Control of Ovulation - NCBI - NIHncbi.nlm.nih.govAug 5, 2018 ... For complete coverage of this and related topics, please visit www.endotext.org. Go to: THE FOLLICULAR PHASE (Fig.1). Figure 1. .…
- Understanding the Phases of the Menstrual Cycle - Cluehelloclue.comLearn about the different phases of the menstrual cycle and how hormones influence each stage, from menstruation to ovulation.
- Physiology, Menstrual Cycle - StatPearls - NCBI Bookshelf - NIHncbi.nlm.nih.govSep 27, 2024 ... Hormonal regulation begins in the hypothalamus, where gonadotropin-releasing hormone (GnRH) is secreted in an increased, pulsatile fashion ...
- Menstrual cycle | Description, Phases, Hormonal Control, Ovulation ...britannica.comOct 1, 2026 ... The cycle has four phases: menstrual, postmenstrual, proliferative, and secretory. During the cycle, the ovaries secrete estrogen and ...
- Menstrual Cycle (Normal Menstruation): Overview & Phasesmy.clevelandclinic.orgDec 9, 2022 ... These hormones cause the lining of your uterus to thicken. This happens so that if a pregnancy would occur, an…
- 43.4 Hormonal Control of Human Reproduction - Biology 2eopenstax.orgMar 28, 2018 ... Describe the roles of male and female reproductive hormones; Discuss the interplay of the ovarian and menstrual cycles; Describe the…
- Influence of hormonal control on LH pulsatility and secretion in ...pubmed.ncbi.nlm.nih.govSuppression of progesterone and androgen concentrations during the follicular phase of the menstrual cycle should be a major objective in these patients.
- Menstrual Cycle and Hormonal Contraceptives in Female Athletespmc.ncbi.nlm.nih.govNotably, even when menstrual cycle phases are verified using direct hormonal ... Altered postural control during the luteal phase in women with premenstrual ...
- Emotion regulation ERPs differ based on menstrual cycle phase and ...pubmed.ncbi.nlm.nih.govWhile hormonal contraceptives (HCs) like oral contraceptive pills (OCs) and intrauterine devices (IUDs) can reportedly influence mood, the evidence is mixed ...
- How to study the menstrual cycle: Practical tools and ... - PMC - NIHpmc.ncbi.nlm.nih.govThe menstrual cycle phases are characterized by predictable fluctuations of ovarian hormones ... Age-related changes in the regulation of luteinizing hormone ...
- Menstrual Cycle - Women's Health - Merck Manual Consumer Versionmerckmanuals.comThe increasing estrogen also begins to prepare the uterus and stimulates the luteinizing hormone surge. On average, the follicular phase lasts about 13 or…
- Hormonal Control Of Reproduction - MCAT Content - Jack Westinjackwestin.comThe pattern of activation and inhibition of these hormones varies between phases of the reproductive cycle. The female reproductive cycle or menstrual cycle is ...
- Hormones of the Menstrual Cycle – Human Reproductioniastate.pressbooks.pubThe flowchart on the top left shows the hormonal regulation Figure 2. Hormonal action during ovarian and Uterine cycles. Menstrual phase. High progesterone ...